

By Amber Daly
Download the full article as a PDF
IRA & Drug Price Negotiation Program Background
What is the IRA?
Inflation hit historic highs, beginning in 2021 and carrying into 2022, due to the COVID-19 pandemic. As a result, the Biden Administration, having just taken office in 2021 was forced to address rising costs for the Federal Government as well as millions of Americans.
One of the ways the Administration worked to address these issues was to introduce and eventually sign into law, the Inflation Reduction Act (IRA) in 2022. This piece of legislation provisioned significant funding across several sectors and programs (beyond healthcare), investing in initiatives that would eventually lead to cost savings for the Federal Government and consumers alike.
One of the key areas of focus within the IRA is broadly referred to as Drug Pricing Reform. Under this umbrella, funding was established to the tune of $288B1 to make improvements to Medicare. Within the IRA, there are 4 main components related to Drug Pricing Reform, including: Medicare Part D Improvements, Medicare Drug Price Negotiation, Inflation Rebates in Medicare, and Changes to Medicare Part B.
In this first installment of our white paper series on IRA, we’re tackling all things Drug Price Negotiation and Maximum Fair Price which is a key component of the price negotiation.
What is the Drug Price Negotiation Program?
Federal drug expenditures in 2022 reached upwards of $400B, with 22% of the costs traced back to just 10 drugs.2 Over the last several decades there have been numerous pieces of legislation introduced at the federal and state levels aimed at containing prescription drug costs, but till now, the Centers for Medicare and Medicaid Services (CMS) was statutorily prohibited from directly negotiating drug prices. With the passing of the IRA, Medicare Drug Price Negotiation (or as we’ll refer to it throughout this paper as MFP – Maximum Fair Price) grants authority to CMS to negotiate drug prices directly with manufacturers. This establishes legally binding price ceilings, or Maximum Fair Prices, for selected Part D and Part B drugs that are high-expenditure, single source drugs without generic or biosimilar competition.
The primary objectives of establishing these MFPs include:
- Cost Controls: By negotiating lower prices for high-expenditure drugs, CMS aims to decrease the financial burden on the Medicare program and taxpayers, and ensure the sustainability of the program long-term
- Patient Affordability: The negotiated prices are designed to lower out-of-pocket costs for Medicare beneficiaries, particularly those requiring chronic or high-cost treatments
- Price Transparency: By formalizing the negotiation process, the program seeks to create a more transparent system where drug prices reflect clinical value and production costs
As the Drug Price Negotiation Program moves from policy design into live operations, the industry is beginning to see its first real-world results. Whether the Program ultimately achieves its broader objectives around cost control, patient affordability, and transparency will continue to be evaluated as additional cohorts enter the Program.
MFP: Price Negotiation Process
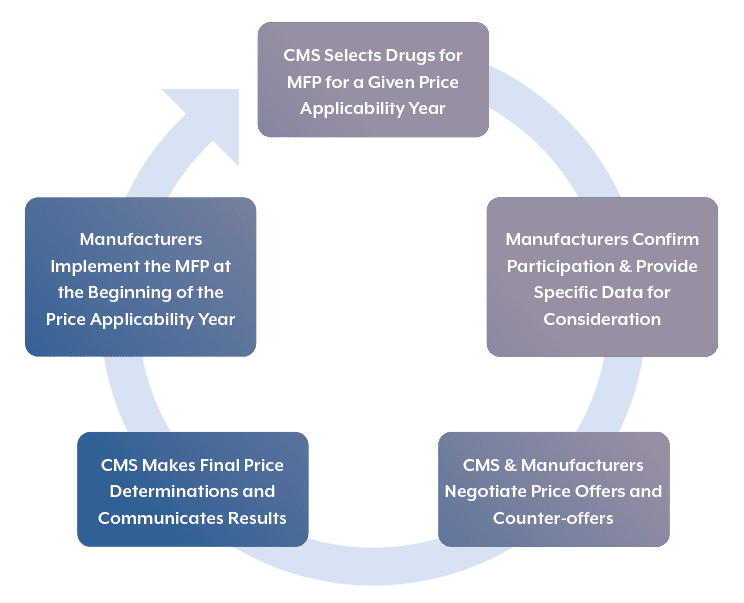
The Drug Price Negotiation Program operates on an annual cycle to select, negotiate / renegotiate, finalize, and effectuate MFPs. With the first MFPs effective in 2026, these activities increasingly overlap across price applicability years as manufacturers simultaneously operate live MFPs, prepare for future effectuation, and participate in new negotiation cycles.
Drug Selection Summary
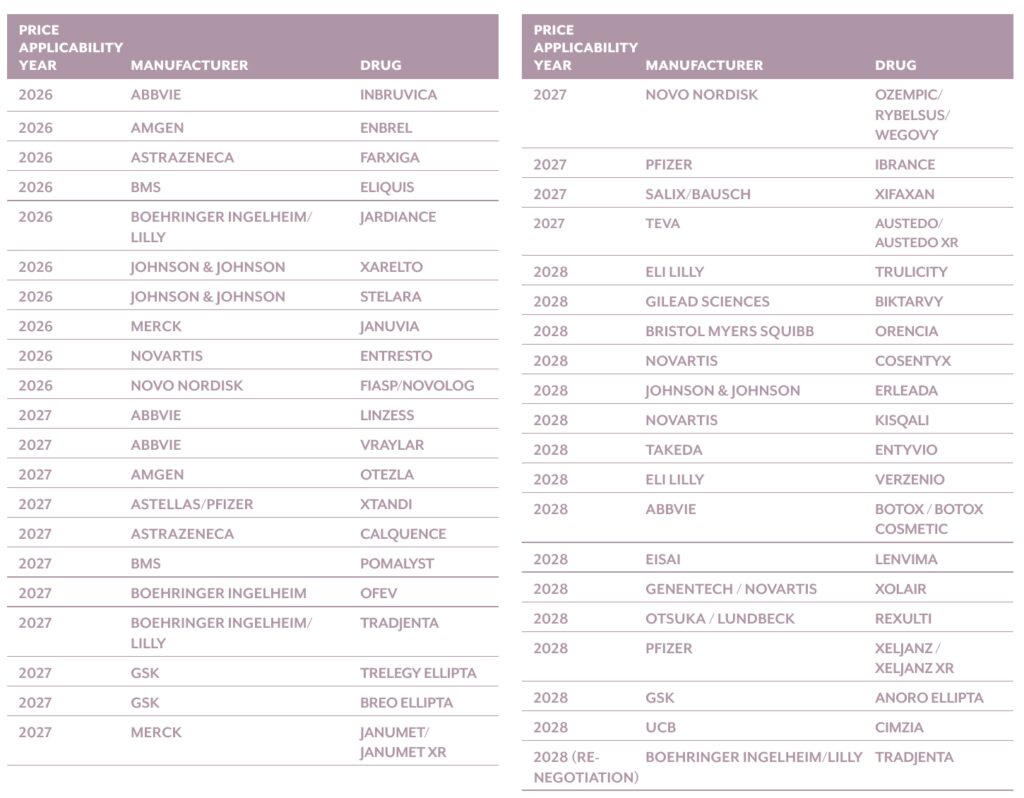
The first step in the negotiation process is for CMS to identify and communicate its plans for drugs included in the price applicability year under review. Each year beginning in 2026 a new set of MFP drugs will be active, expanding the program in number of drugs as well as the parts of Medicare impacted over time. MFPs are active for the first 10 Part D drugs; negotiated prices have been finalized for 15 additional Part D drugs effective in 2027; and CMS has selected 15 Part B and/or Part D drugs for 2028, marking the first inclusion of Part B drugs. CMS also selected the Program’s first drug for renegotiation for 2028.
How Are Drugs Selected?
CMS analyzes prescription drug event (PDE) data for Part D drugs and claims data for Part B drugs to determine total expenditures for negotiation-eligible drugs. From that data, the top 50 drugs with the highest expenditures are ranked and evaluated based on the following criteria:
Drug Type and Market Exclusivity:
- Small-Molecule Drugs: Eligible if approved by the FDA more than 7 years prior and without generic competition
- Biological Products: Eligible if licensed by the FDA over 11 years ago and lacking biosimilar competition
Exclusions:
- Orphan Drugs: Drugs designated for one or more rare diseases or conditions under section 526 of the FD&C Act are excluded if all approved indications are for one or more of those designated rare diseases or conditions. If a drug later loses its orphan drug exclusion, its 7- or 11-year eligibility period generally begins when it ceases to qualify for the exclusion
- Low-Spend Drugs: Drugs with less than $200 million in combined annual expenditures under Medicare Parts B and D
- Plasma-Derived Products: Biological products derived from human whole blood or plasma, as indicated on their labeling
Additional Selection Considerations:
- Small Biotech Exception: Manufacturers can apply for an exception if a drug represents a significant portion of their revenue and meets specific criteria
- Biosimilar Delay: If a biosimilar is expected to enter the market imminently, the reference biological product may be excluded from negotiation
- Bona Fide Marketing: CMS conducts ongoing assessments to determine whether meaningful competition exists, ensuring that any generic or biosimilar products are marketed on a bona fide basis
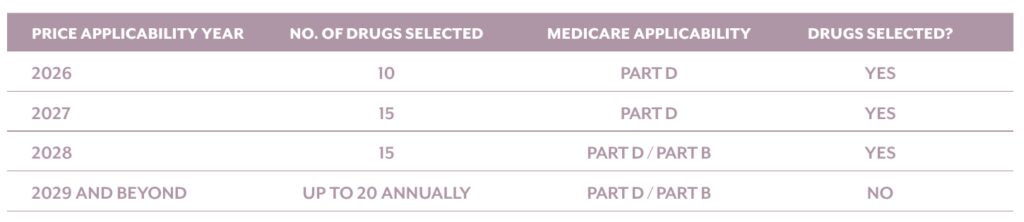
Drugs meeting the above criteria have been selected for Price Applicability Years 2026, 2027, and 2028, depicted in the table below.
Once CMS makes its selections, manufacturers have a short window to sign agreements confirming participation in the program. While this step offers the illusion that the program is voluntary, failure to participate is likely to result in extreme consequences. The penalties are so significant they would push much higher costs to patients, limit patient access, and stifle revenue growth, almost guaranteeing, by design, a manufacturer’s participation. To date, manufacturers of all drugs selected for the 2026, 2027, and 2028 negotiation cycles have elected to participate.
Penalties Include:
- Civil monetary penalties calculated as ten times the difference between the price charged and the MFP, multiplied by the number of units sold
- Significant excise taxes starting at 65% of the product’s U.S. sales and increasing by 10% each quarter, up to a maximum of 95%
- Withdrawal of a manufacturer’s portfolio from Medicare and Medicaid programs
Price Negotiation & Setting
When drug selection is complete for a given price applicability year, the price negotiation process towards the MFP starts immediately.
Manufacturers must act quickly once they are made aware their drug(s) has been selected for the Program. They must first confirm participation by entering into an agreement with CMS to negotiate prices. And secondly, they must prepare supporting drug-specific data submissions including research & development costs; production & distribution costs; federal financial support for drug discovery and development; patent and exclusivity information, including pending and approved patents, FDA exclusivities, and FDA applications; and market, revenue, and sales volume data. As updates or revisions to the data become necessary, the manufacturer must report them to CMS in a timely fashion throughout the negotiation period.
Once the information is provided, CMS will host public engagement sessions with patient-focused roundtables and town hall meetings. During this period, the manufacturers will also have an opportunity to discuss their data submissions directly with CMS.
All of the information gathered till this point is taken under consideration while CMS derives their initial offer. Fortunately for manufacturers, there are some guardrails in place to ensure the MFP is “fair”. The Program sets an upper limit for the MFP, determined by the lowest of the following:
- Part D drug: Enrollment-weighted negotiated price (net of all price reductions, including rebates)
- Part B drug: Average sales price (the price paid by non-federal purchasers in the U.S., including rebates, excluding Medicaid rebates)
- Non-FAMP: A percentage of the non-federal average manufacturer price (the price wholesalers pay manufacturers for drugs distributed to non-federal purchasers). The percentage of non-FAMP varies based on the years since FDA approval or licensure:
- 75% for small-molecule drugs and vaccines 9-12 years after approval
- 65% for drugs 12-16 years after approval or licensure
- 40% for drugs more than 16 years after approval or licensure
Once CMS determines the price and sends the initial offer, it’s off to the negotiation races! Hopefully by this point manufacturers have had time to engage market access, legal, finance, and other commercial and government operational teams to work on forecasts and simulations designed to inform decisions they may make based on the offer received.
While much of the negotiation process continues to take place behind closed doors, manufacturers now have two completed negotiation cycles to draw from as they evaluate CMS’s approach and develop their own negotiation strategies. With the third negotiation cycle now underway for IPAY 2028, several manufacturers enter the process with experience from prior negotiation cycles. This round also introduces new considerations, including the first Part B selected drug and the Program’s first renegotiation of a previously negotiated drug.
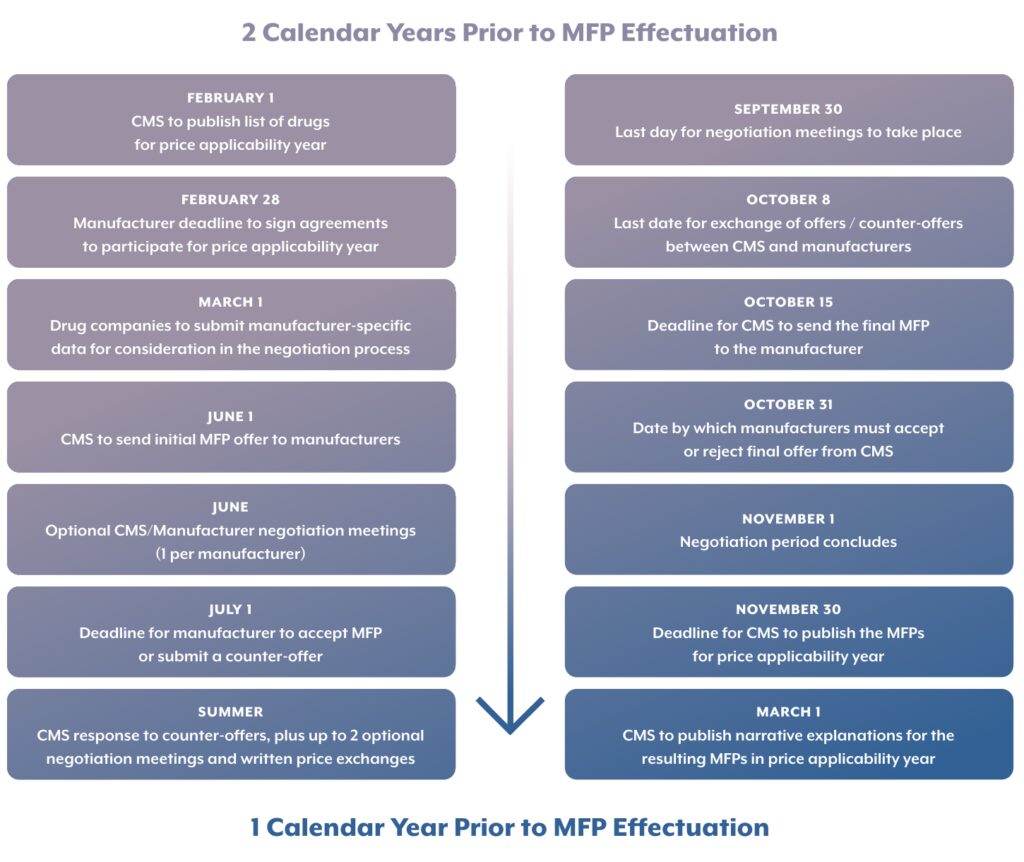
Throughout the negotiation process, the goal is for CMS and the manufacturer to reach an amicable MFP, however, if an agreement is not reached within the designated timeframe, CMS has the authority to unilaterally set the MFP. After the final price is determined and announced, the manufacturer has approximately one year to implement processes and tools to effectuate the MFP at the start of the Price Applicability Year.
A summary of drug price negotiation activities and timelines for a given Price Applicability Year is captured below:
MFP Effectuation
So CMS has determined the final MFP for your drug, now what?
With the first round of MFPs live since January 1, 2026, effectuation has moved from design into day-to-day operations. Manufacturers are now managing MFP access, MTF data exchange, payment timing, disputes and adjustments, and interactions with existing government and commercial pricing programs. At the same time, manufacturers with 2027 and 2028 selected drugs are applying lessons from the first year of operations to readiness planning. The operational burden continues to span people, process, data, and technology, but the focus has shifted from selecting an approach to sustaining compliant execution at scale.
CMS permits manufacturers to provide access to the MFP prospectively or retrospectively. For Part D, the first year of live operations is providing practical experience with the MTF-supported retrospective model and the data, payment, and exception-management processes required for effectuation. For 2028, CMS has also issued draft guidance describing effectuation requirements for the Part B component of the selected cohort, extending the operational discussion beyond Part D dispensing entities and introducing considerations specific to Part B providers. We’ll examine both effectuation approaches holistically, including the differences between them and pros and cons of each.
- Prospective Effectuation: The MFP is applied upfront at the package level, ensuring that entities purchase drugs at the reduced price at the time of sale
- Retrospective Effectuation: The MFP is applied after the sale at the unit level, where price adjustments are refunded back via rebates, based on the actual acquisition cost
Each option carries operational, financial, and compliance implications, as well as potential conflicts with 340B, Medicaid, and commercial contracts.
Prospective Effectuation
Prospective effectuation ensures that the MFP for eligible drugs is honored as an on-invoice discount where the MFP is extended at the time of invoice.
Key Characteristics:
- Pricing Level: MFP applied at the saleable package level
- Timing: The price adjustment happens upon the payment of the invoice
- Operational Considerations:
- Updating contract pricing structures with supply chain partners
- Communicating pricing changes in advance to ensure correct pricing is applied
- Ensuring wholesaler and distributor compliance in passing through the MFP. If multiple price points exist for a single dispensing entity, how will a wholesaler/ distributor know to honor an MFP vs. 340B vs. Commercial Payer price without knowing at the time of sale, the intended program or recipient?
- Prospective effectuation may require dispensing entities and supply-chain partners to distinguish inventory and transactions associated with MFP-eligible individuals from other pricing programs, creating inventory, eligibility, and reconciliation considerations
- Master Data Management overhead to create/manage accounts for dispensing entities as customers in revenue management and ERP systems to ensure MFP eligibility is communicated throughout the supply chain
Pros
- Simplifies program compliance, eliminating the need for retrospective rebate adjudication & settlement in a short cycle time of 14 days
- Relies on existing infrastructure, operating a model similar to common chargebacks processing that happens against contracted pricing for other customer types/programs
- Eliminates cash flow concerns for dispensing entities, providing real-time discounts
Cons
- Heavy burden on manufacturers and wholesalers to manage master data and contract changes as well as increased chargeback processing volumes
- Potential pricing conflicts with 340B and Medicaid due to overlapping price reductions that become challenging to retroactively resolve once the price is already honored
- Dispensing entities to carefully monitor inventory to ensure the MFP purchased drug is being dispensed to the intended program recipient (without oversight, there is a lot of room for error)
- Lack of standard identifiers to communicate MFP-specific transactions which can result in incorrect extended pricing throughout the supply chain: Manufacturer > Wholesaler > Dispensing Entity > Patient, and could ultimately result in noncompliance and associated consequences for manufacturers
- Package pricing and sales data doesn’t align exactly to utilization, therefore requiring conversions to ensure the right price
- Practically speaking, the lack of transparency in the claim and sales data to create a connection point linking an eligible patient to given price point at the time of invoice, is practically impossible, calling into question whether this ‘option’ is even possible
Retrospective Effectuation
Retrospective effectuation is the process by which manufacturers will retroactively calculate refunds in the form of rebates to dispensing entities based on utilization claim data.
Key Characteristics:
- Pricing Level: Applied at the unit level where adjustments are made based on actual acquisition cost, unites dispensed and the MFP
- Timing: Refunds for the difference between acquisition cost and the MFP occurs after the drug is dispensed and must be paid within a 14-day window
- Operational Considerations:
- Implement processes and technology solutions to ingest the claim data from dispensing entities via the MTF (described below), scrub and validate the data, calculate the rebate amount, and process payment
- Claims calculated using SDRA (Standard Drug Rebate Amount) which is based on WAC, however, that may not represent the actual acquisition cost if there are other eligible contract prices
- Retrospective MFP refunds are subject to a 14-day prompt-payment requirement once the applicable MTF data is received. Compared with traditional commercial and government rebate cycles, this compressed timeline places greater emphasis on automated validation, exception handling, dispute workflows, payment controls, and operational monitoring
- Manufacturers must determine how to establish payment remittance – either using MTF PM (described below), or another mechanism. If the MTF PM is not utilized, claim level payment details must still be submitted to the MTF DM
- If a manufacturer determines to remit payments outside the MTF PM, they must also keep record of debit/credit activity to facilitate reversals or adjustments to claims . A process for handling disputes with individual dispensing entities must also be established, in the event the manufacturer chooses to not enroll in the MTF PM
- Need a way to determine cross-program and dual-patient eligibility to correctly calculate the rebate amount (e.g. Inflation Rebates, Commercial/Medicaid/ Medicare/340B overlapping eligibility)
- To anticipate MFP impacts on Gross-to-Net, manufacturers will need to re-assess rebate accrual rates and forecasting models to account for the impact of MFPs from changes in pricing, volume/utilization, and rebate liabilities. Current models and strategies for forecasting Best Price, Medicaid, 340B liabilities may also need to be adjusted for any unintended cascading impacts from the MFP
Pros
- Enables due diligence on the manufacturer side to validate claims data and dispute before payment is extended, providing a bit more control over the release of funds
- Manufacturers can maintain existing contracts with various supply chain partners
- Manufacturers have increasingly implemented dedicated technology, vendor services, and operating models to support MFP refund processing. While many capabilities build on existing rebate-processing concepts, the MTF data model, 14-day payment requirement, eligibility logic, and cross-program interactions make MFP a distinct operational process rather than a simple “lift and shift.”
Cons
- High administrative burden / cost to process, either requiring technology solutions to support or 3rd party providers to process on a manufacturer’s behalf
- Medicaid SDRA methodology may misalign WAC-MFP vs. acquisition-based rebates
- Potential Medicaid best price conflicts, depending on how acquisition costs are calculated for rebates
- Aggressive 14-day turnaround time, beginning when the MTF DM sends the claim-level data. If timelines are not met and identified via an audit or complaint, CMS will investigate and potentially levy civil monetary penalties equal to ten times the difference between the price paid and the MFP, multiplied by the total number of units dispensed
What is the Role of the MTF in MFP Effectuation?
The Medicare Transaction Facilitator (MTF) is now an operating component of MFP effectuation, facilitating data exchange and, where elected, payment activity between manufacturers and dispensing entities. Beginning in 2028, the MTF will also support MFP effectuation for selected drugs payable under Part B, with CMS adapting the framework to account for structural differences between Part D dispensing and Part B furnishing or administration.
The MTF is structured into two distinct modules, each serving a specific function:
Data Module (MTF DM)
- Function: Facilitates the exchange of data among stakeholders, including pharmacies, pharmacy benefit managers (PBMs), manufacturers, and CMS including the following:
- Claim-level data confirming dispensation of drugs to MFP-eligible individuals
- Initiates the 14-day prompt payment window
- Rebate payment elements, including payment confirmation and amount
- Includes the Standard Drug Rebate Amount (SDRA), calculated as WAC minus MFP
- Generates Electronic Remittance Advice (ERA) for payments processed through MTF PM
- Mandatory Participation: All manufacturers of drugs selected for price negotiation are required to participate in the MTF DM to ensure proper data flow and compliance
Payment Module (MTF PM)
- Function: Manages the financial transactions related to MFP effectuation, such as:
- A fund transfer mechanism for manufacturers (electronic and paper check)
- A credit/debit ledger system for tracking MFP refunds, reversals, adjustments, and claim revisions
- Payment tracking for manufacturers who opt to make payments outside of MTF PM
- Optional Participation: Manufacturers have the discretion to participate in the MTF PM. If they opt out, they must establish alternative mechanisms to handle the financial aspects of MFP effectuation
Data Exchange and Privacy
The MTF handles sensitive information, including drug pricing details, transaction records, and beneficiary data. CMS has implemented protocols to ensure that all data exchanges comply with applicable privacy and security regulations, safeguarding the information managed by the MTF. Data that will be passed includes (but not limited to):
- Drug Identifiers (NDC, Package Level Data, etc.)
- Transaction Details (Date of Sale, Dispensing Entity, Claim Number)
- Beneficiary Eligibility Status for MFP
- Pricing Information (WAC, Contracted Price, MFP Applied Price)
- Manufacturer Rebate Data (for retrospective effectuation)
Manufacturer Response to MFP and Looking Ahead
Since the enactment of the IRA, several pharmaceutical manufacturers have initiated legal challenges against the Drug Price Negotiation Program, particularly targeting the MFP provision. These lawsuits underscore the industry’s concerns over the constitutionality and economic implications of government-mandated price negotiations. Among the companies that have pursued litigation are Merck, AstraZeneca, Bristol Myers Squibb, Johnson & Johnson’s Janssen Pharmaceuticals, Teva Pharmaceuticals, Novo Nordisk, Boehringer Ingelheim, Novartis, and Astellas Pharma. Additionally, industry trade organizations such as the Pharmaceutical Research and Manufacturers of America (PhRMA) and healthcare providers like the National Infusion Center Association have also challenged the law.
A central theme in several of these lawsuits has been the argument that the IRA’s price negotiation framework constitutes an unconstitutional taking under the Fifth Amendment. Other challenges have asserted First Amendment, due process, excessive fines, and other constitutional claims. To date, these broader constitutional challenges have largely been unsuccessful, with federal appellate courts repeatedly ruling in favor of the government.
The legal landscape continued to shift in 2026. In May, the U.S. Supreme Court declined to hear several manufacturer challenges to the Program, leaving lower-court decisions in favor of the government in place. This included AstraZeneca’s challenge after the Third Circuit had rejected its due process claims and found that it lacked standing to pursue certain Administrative Procedure Act claims.
However, litigation surrounding the Program has not ended. Manufacturers continue to pursue more targeted challenges involving CMS’s interpretation and implementation of specific provisions of the IRA, including how drugs are defined and aggregated for negotiation eligibility and how CMS determines whether generic or biosimilar competition is bona fide marketed. New litigation has also continued to emerge as additional drugs are selected for negotiation.
As a result, the legal landscape has evolved from broader uncertainty around the viability of the Drug Price Negotiation Program toward more targeted questions regarding how CMS interprets and administers individual provisions. At the same time, the Program has continued to advance across administrations, with MFPs now in effect for the first cohort, negotiated prices established for IPAY 2027, and negotiations underway for IPAY 2028.
Looking Ahead
While much of this is not within a manufacturer’s full control, there are some things that are. Cross-functional organizational support and internal alignment remain critical success factors, whether a manufacturer has a selected drug today or is assessing future exposure. What has changed is the number of MFP horizons that may need to be managed at once. Manufacturers may simultaneously be effectuating an active MFP, preparing another selected drug for a future price applicability year, participating in negotiation or renegotiation, and assessing pipeline or portfolio exposure to future selection.
Pricing committees, brand teams, market access, P&C operations, finance, legal, data, and technology therefore need clear ownership across forecasting, negotiation strategy, evidence development, operational readiness, MTF execution, payment controls, compliance monitoring, and cross-program impacts. Even without a selected drug, launch teams, brand strategy, market access, finance, and others must evaluate how actions and decisions across the commercialization continuum may need to adjust for direct and indirect MFP impacts. MFP may appear self-contained to one drug at a time, but its reach extends across the broader portfolio and operating model.
The next phase of MFP will be defined less by whether the Program launches and more by how it scales. Key areas to watch include:
- Introduction of Part B into the Program in 2028
- Evolution of CMS’s renegotiation framework
- Rulemaking for 2029 and subsequent years
- Lessons from live MTF operations and 14-day payment performance
- Increasingly complex interactions with 340B, Medicaid, commercial contracting, and other federal pricing policies
That overlap is becoming more tangible: under HRSA’s revised 340B Rebate Model Pilot Program, qualifying manufacturers of selected IPAY 2026 and 2027 MFP drugs may voluntarily seek approval to effectuate the 340B ceiling price through a claims-based rebate model beginning January 1, 2027. The pilot is specifically intended, in part, to support nonduplication between 340B and the Medicare Drug Price Negotiation Program, adding another operational intersection manufacturers will need to manage across eligibility, claims validation, rebate calculation, payment, and duplicate-discount controls. For manufacturers, the strategic question is increasingly how MFP and adjacent pricing reforms change lifecycle economics, contracting strategy, launch planning, loss-of-exclusivity assumptions, and investment decisions across the broader portfolio.
Sources
- “SUMMARY: THE INFLATION REDUCTION ACT OF 2022”,
Democrats.Senate.gov, https://www.democrats.senate.gov/imo/media/doc/
inflation_reduction_act_one_page_summary.pdf ↩︎ - “Medicare Part D Spending By Drug”, Data.CMS.gov,
https://data.cms.gov/summary-statistics-on-use-and-payments/medi-
care-medicaid-spending-by-drug/medicare-part-d-spending-by-drug ↩︎